




★ ★ ★ ★ ★★ ★ ★ ★ ★ Verified rating
We left very happy with the doctor-patient relationship
Its medical name is renal cell carcinoma (RCC). The subtype of RCC will determine, among other factors, the appropriate treatment. At ROC Clinic, we have all the available technology to treat kidney cancer.
Kidney cancer is a malignant cell growth that occurs in the kidneys and accounts for about 3% of all cancer diagnoses worldwide. Its medical name is renal cell carcinoma (RCC).
“Kidney cancer” is a general term, as there are many types of kidney tumors and different stages of the disease. Treatment will depend on the specific characteristics of the tumor.
In recent years, thanks to imaging tests such as urinary tract ultrasound and CT scans, the number of diagnoses at early stages has increased, leading to higher survival rates. Likewise, survival rates for kidney cancer have also increased, partly due to improved treatments in both early stages (surgery) and more advanced stages (targeted systemic therapies). Nephron-sparing surgery (or partial nephrectomy) allows for the removal of only the tumor, preserving most of the organ and providing the patient with a better quality of life in the long term. We can state that more than 90-95% of patients will be cured with surgery alone when the tumor is diagnosed at a localized stage.
In terms of its epidemiology, kidney cancer is more common in men than in women, and most people are diagnosed between the ages of 60 and 70.
At ROC Clinic we have all the technology available on the market to treat kidney cancer, such as the da Vinci robot , laparoscopy and ablative treatments, among others.
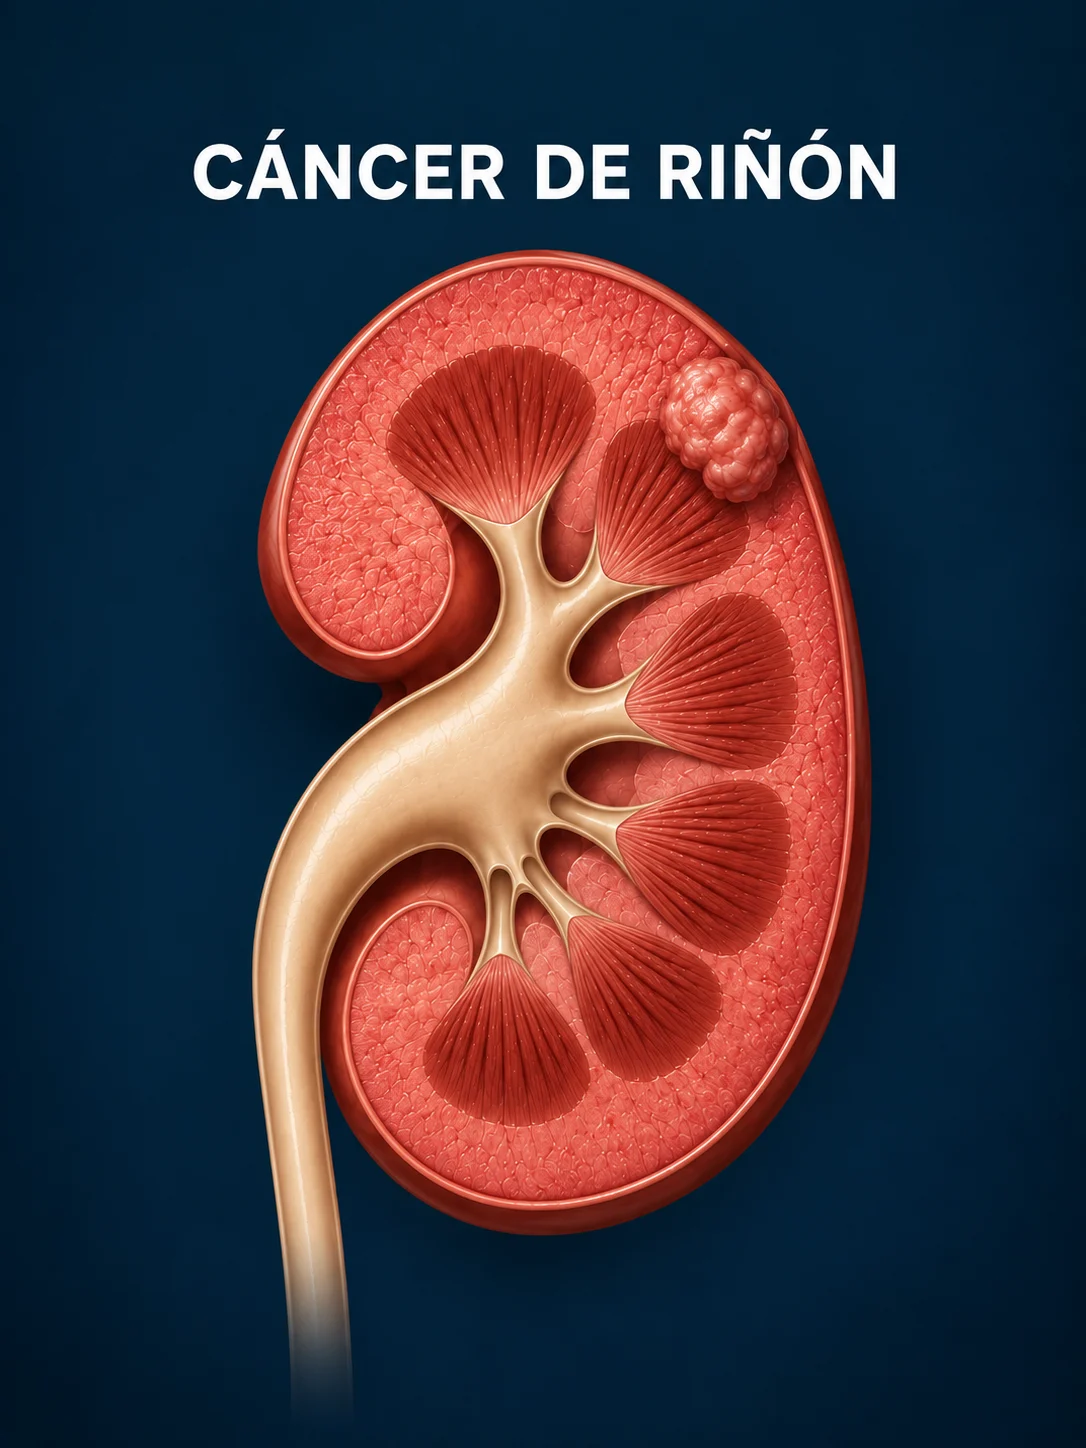
Kidney cancer usually does not present symptoms in its early stages. For this reason, most kidney tumors are diagnosed incidentally during diagnostic tests performed for other reasons, when the tumor has not yet caused any symptoms. When tumor growth occurs and the disease is in a more advanced stage, it may present a series of symptoms:
Scientists continue to investigate the factors that cause kidney cancer and ways to prevent it. Studies conducted so far conclude that there is a link between kidney cancer and the following factors:
Kidney tumor grading is used to estimate your individual prognosis. Based on this individualized prognosis, your doctor will discuss the best course of treatment for you. Kidney cancers are generally assigned a grade from 1 to 4.
The treatment for kidney cancer will depend on the stage of the cancer, the patient's age, and any other health problems they may have. Whenever technically and oncologically feasible, the aim will be to remove only the tumor while preserving the kidney.
For treatment, it is necessary to differentiate between localized and metastatic tumors:
It is the recommended treatment for patients whose disease is in stage I. It consists of removing the entire renal tumor, preserving as much of the organ as possible to avoid subsequent renal failure; that is, only the tumor is removed and the rest of the healthy renal tissue is preserved.
This treatment achieves 80-100% disease-free survival rates at 5 years. It is the most appropriate treatment, whenever technically feasible, for tumors smaller than 7 cm, in patients with tumors in both kidneys, or in patients with a single kidney. Surgery can be performed via open, laparoscopic, or robotic approaches, depending on the specific case.
Robotic surgery for the treatment of localized kidney cancer using partial nephrectomy allows for the treatment of tumors of any complexity using a minimally invasive technique with high precision and excellent oncological outcomes. This approach also offers faster recovery, a lower risk of bleeding, less postoperative pain, and a shorter hospital stay. At ROC Clinic, we have both of the two robotic systems available on the market: d a Vinci and Toumai.
This is the recommended treatment for patients in whom partial surgery is not possible. It consists of the complete removal of the affected kidney, preserving the adrenal gland unless it is infiltrated by the tumor. In cases where lymph nodes are found to be affected, a lymphadenectomy (removal of lymph nodes near the kidney) will be performed. Radical nephrectomy can also be performed via open, laparoscopic, or robotic approaches, depending on the characteristics of each case.
Sometimes, surgery may not be the best option for you. Close monitoring of the tumor can be performed on very elderly patients, those in poor health, or those with tumors smaller than 3-4 cm.
During this period of active surveillance, regular visits with imaging tests will be scheduled. To determine if active surveillance is appropriate and to refine your individualized diagnosis, your urologist may recommend a biopsy of the kidney tumor. If tests performed during active surveillance show that the tumor is growing rapidly, or if you develop symptoms that may indicate the disease is progressing, the urologist will immediately plan salvage treatment, primarily involving surgery.
In people who are not suitable for surgery due to significant risk, either because they are very old or have other illnesses, kidney cancer can be treated through ablation. This procedure applies energy to the tumor laparoscopically or percutaneously using radiofrequency or cryotherapy. It can also be performed in people with tumors smaller than 3 cm in certain locations.
When the tumor progresses locally, a thrombus with a tumor component may appear in the renal vein, or even in the vena cava. In these cases, nephrectomy and excision (removal) of the entire tumor thrombus are necessary, sometimes requiring the collaboration of cardiac surgeons.
This procedure is performed in cases of metastatic kidney cancer, meaning when kidney cancer has spread to other organs or lymph nodes. In metastatic disease, the kidney tumor is called the primary tumor, and secondary tumors in other organs are called metastases. When this occurs, a cytoreductive nephrectomy is performed with the aim of curing the patient or prolonging their survival, combining surgery with systemic therapies (immunotherapy, anti-angiogenic drugs). It involves removing as much of the tumor as possible to increase the chances of success with immunotherapy and other targeted therapies. This removal also allows for the elimination of surrounding tissue that may contain cancer cells.
Chemotherapy has limited use in treating kidney cancer. However, immunotherapy and drugs that stimulate the immune system help attack cancer cells and significantly improve survival rates. Immunotherapy can cause side effects, depending on the medication, which usually disappear after treatment ends: fatigue, upset stomach, fever, chills, and skin rashes.
Once any of these treatments is completed, it is important to attend regular check-ups to monitor progress through diagnostic tests.
We treat our patients at the ROC Chamberí clinic and in the HM Hospitals network of centers in Madrid: Sanchinarro, Montepríncipe, Madrid Río, Rivas, Puerta del Sur, Nuevo Belén, Policlínico HM Moraleja and Nuevo Norte.

Coming soon
We treat our patients at the ROC Chamberí clinic and in the HM Hospitals network of centers in Madrid: Sanchinarro, Montepríncipe, Madrid Río, Rivas, Puerta del Sur, Nuevo Belén, Policlínico HM Moraleja and Nuevo Norte.
Coming soon

We left very happy with the doctor-patient relationship
JG August 6, 2026
Our patients' trust reflects our commitment to providing excellent, personalized, and attentive urological care. Every experience motivates us to continue improving and offering the care and support each patient needs.


Excellent urological clinic due to the professionals who work there.
A highly professional clinic, with a very high scientific level and advanced technology. They helped me solve my urological problem.

I can only say one thing, the urology girls are the best you can find in this...
I want to express my gratitude to the Roc team, especially Dr. David Carracedo, for their professionalism, the...

Excellent care, both from Dr. Rojo and Dr. Espinales on a medical level and from the staff of...

Top 100 deal

I've been coming to the Urology department at HM Monteprincipe for a long time and I'm very happy with the care I receive from...
“Doctor, my urine smells strong. Is this normal?” This is one of the most common questions in urology, and in most cases, the…


Search
Type a keyword and press Enter.


