Prostate Cancer

Prostate cancer is the most frequently diagnosed cancer in men.

Prostate cancer is a very common disease that affects 25% of men over 50 years of age and 80% of those over 80 years of age.

( * Required fields)

What is it?

Prostate cancer is a disease in which malignant (cancerous) cells form in the tissues of the prostate gland . The prostate is a gland in the male reproductive system whose function is to produce a fluid that is part of semen. The prostate is located below the bladder and surrounds part of the urethra. It is about the size of a walnut.

The incidence of prostate cancer diagnosis varies greatly between different geographical areas, which may be related to ethnic factors, the aging of the population, since this incidence depends mainly on age, and the routine use of PSA for screening for this type of tumor.

Family history and ethnicity are associated with a higher incidence of prostate cancer, suggesting a genetic predisposition to the disease. Hereditary prostate cancer is associated with an earlier onset of the disease six to seven years, but the aggressiveness of the disease and its clinical course do not appear to differ.
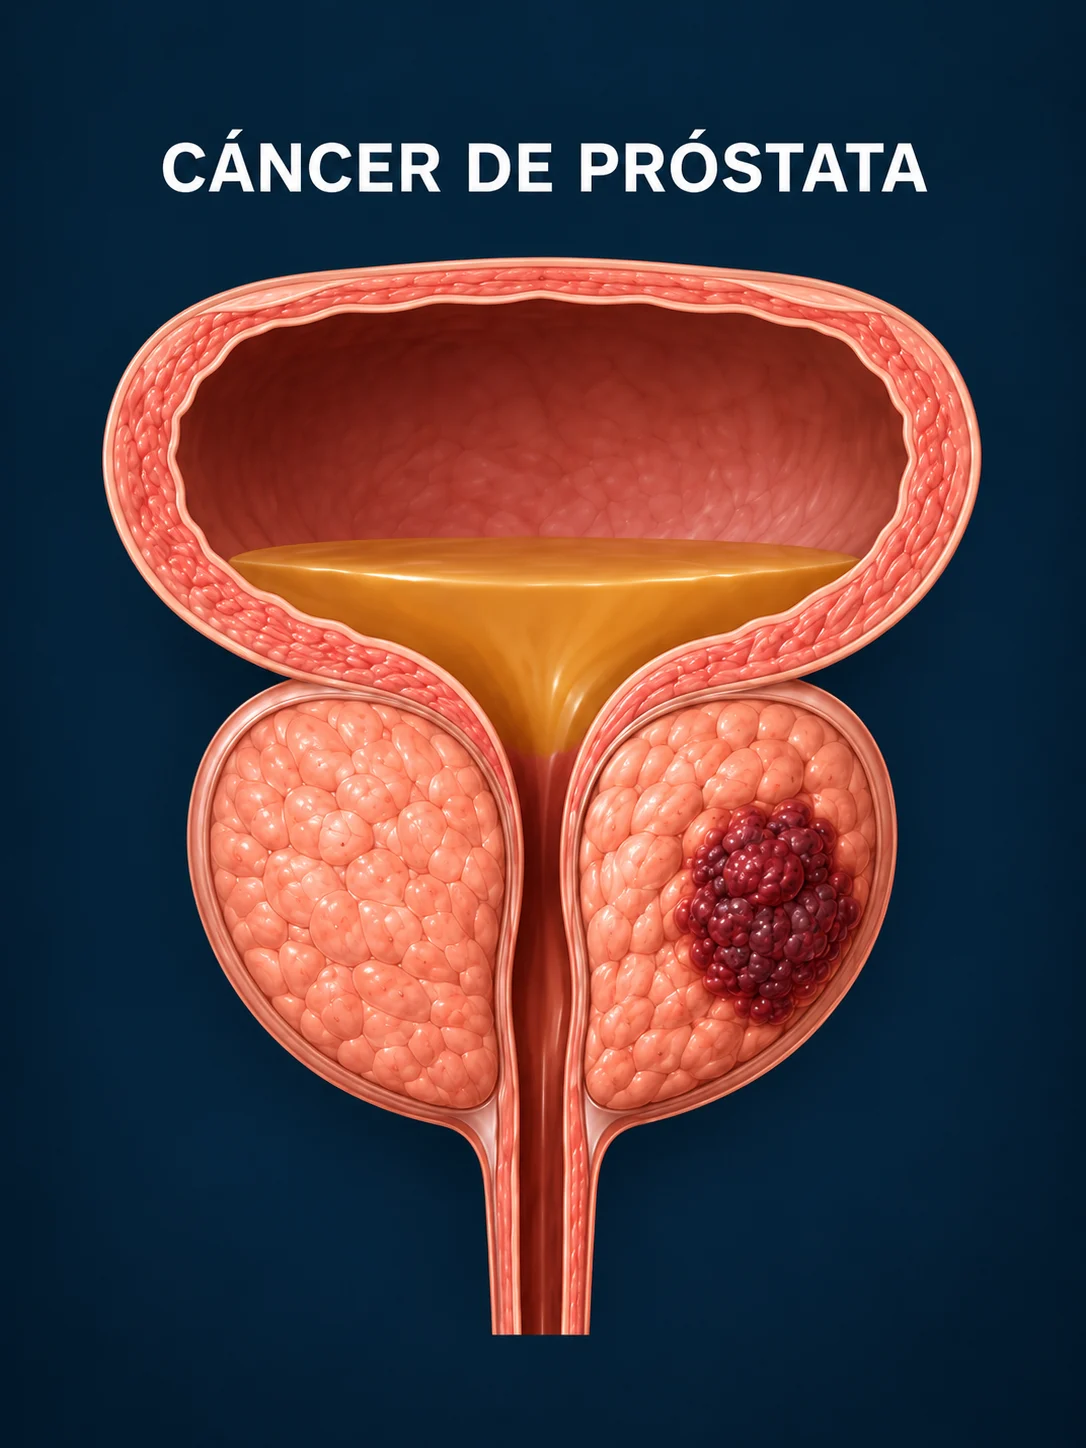
Prostate cancer usually doesn't cause symptoms. Most of the time it's diagnosed before it produces any effects. The symptoms a man with a prostate tumor typically experiences are secondary to benign prostatic hyperplasia (BPH), which often coexists with it.  

  • Painful urination (dysuria).
  • Increased urinary frequency.
  • Weak stream.
  • Sensation of incomplete evacuation.
  • Intermittent urination.
  • Urgency or imperative to urinate.
  • Blood in the urine (hematuria).
  • Blood in the semen (hemospermia).


In some cases, prostate cancer may present at advanced stages . In these instances, the tumor may cause local symptoms such as:

  • Blood in the urine.
  • Great difficulty urinating.
  • Perineal pain.
  • In some cases, it can invade the rectum and cause constipation or changes in bowel habits.
  • If the tumor affects the bladder, urinary urgency, urinary frequency, and urinary discomfort may increase.
  • If the tumor reaches the trigone of the bladder, it can cause obstruction of the ureter and, consequently, lower back pain, colic, ureteral dilation or even the loss of that kidney.
  • If bone involvement occurs, bone pain and even pathological fractures may occur, although this situation is uncommon.

The causes of prostate cancer are unknown, but the main risk factor for developing it is age . There are some associations between racial factors (it is more common in Black men) and a higher rate of prostate cancer diagnosis. In addition, there appears to be a clear association between certain mutations, such as those found in the BRCA1 and BRCA2 genes, and the likelihood of developing prostate cancer.

On the other hand, there appear to be dietary factors , such as obesity, diabetes, alcohol consumption, excessive consumption of red meat, and diets with a high percentage of fatty, fried, dairy, and processed foods.

Tomatoes, lycopene, and soy appear to be protective. The relationship between some micronutrients (selenium and vitamin E) and the development of prostate cancer is debatable.

Prostate cancer often presents no symptoms in its early stages. For this reason, it is very important to see a urologist for early diagnosis of prostate cancer through the following tests:

  • PSA determination. It's a blood test that measures the level of PSA (prostate-specific antigen), a substance naturally produced by the prostate gland. There are no set normal PSA values; instead, age, prostate size, and the number of previous biopsies must be considered. Generally, a PSA level below 1 is considered optimal at any age. A PSA level above 2,5 could indicate an infection, inflammation, enlargement, or prostate cancer.
  • Rectal examination. This test is performed to assess the consistency and size of the prostate gland. If any irregularities are found in the texture, shape, or size of the gland, further tests may be necessary.
  • Urine test. A urine sample is taken to determine if there is hematuria (blood in the urine) or any other abnormality.

Supplementary tests

If any abnormality is detected in the previous tests, further tests, such as the following, may be ordered to determine if you have prostate cancer:

  • Multiparametric magnetic resonance imaging of the prostate. It is a non-invasive test that produces multiple images of the prostate and its behavior. MRI provides a risk assessment for prostate cancer—the PIRADS classification—ranging from 1 (very low) to 5 (very high). This technique also allows visualization of only those tumors that will have clinical significance or pose a risk to the patient's life. MRI also provides very useful information about tumor size, prostate size, tumor stage, its exact location within the prostate, and more.
  • Prostate biopsy: It involves inserting a thin needle into the prostate gland to extract a sample of its cellular tissue for analysis. This analysis confirms or rules out the presence of cancerous cells in the prostate.
  • Prostate biopsy using image fusion. When a PIRADS grade 3 or higher lesion is present, an ultrasound-guided biopsy is usually performed. This generates a real-time 3D model, guiding the sample collection using MRI images. This test allows doctors to know exactly what tumor is present, how far it extends, and its degree of aggressiveness, enabling them to design a personalized treatment plan for each patient. fusion prostate biopsy It not only allows the fusion of multiparametric magnetic resonance imaging (MRI) images, but also PET images, with which a functional assessment of the tumor can be made.
  • Microultrasound. This is a new technology that allows for the replacement of multiparametric magnetic resonance imaging (MRI).It allows real-time visualization of the prostate and guided biopsies. In this way, abnormalities can be detected.  Tumors that MRI does not detect, and visualization of the peripheral area of ​​the prostate. If a suspicious area is detected during the test, a biopsy can be performed immediately.

How can you tell the stage of prostate cancer?

When a biopsy confirms the presence of prostate cancer, the next step is to determine its level of aggressiveness (grade) . A higher grade indicates a more aggressive cancer with a greater likelihood of metastasizing or spreading rapidly. To determine tumor aggressiveness, techniques include:

  • Gleason scoreThe Gleason score is the most common system for grading prostate cancer and helps distinguish between less aggressive and more aggressive tumors. The grade is a number from 1 to 5, with 1 being the most well-differentiated pattern (most similar to normal cells) and 5 the least differentiated (most abnormal). A primary grade is assigned to the tumor cells that make up the majority of the tumor, and a secondary grade to the cells that make up a minority. The Gleason score is therefore the sum of these two most dominant grades. Thus, the potential range of Gleason scores is from 2 (1+1), non-aggressive cancer, to 10 (5+5), highly aggressive cancer.

Apart from these tests, nowadays there are also diagnostic tests that facilitate the detection of prostate cancer before symptoms appear: pro-PSA, 4kallikreins, PCA-3, MDX and others.

How can you tell if prostate cancer has metastasized?

Once the diagnosis has been confirmed, if there is suspicion that the cancer may have spread beyond the prostate, imaging tests such as abdominal CT scans and bone scans may be recommended to rule out lymph node involvement, organ involvement, and bone metastasis.

Tumors with a good prognosis and that are not aggressive:

Active surveillance

In some cases, a prostate cancer with a good prognosis and no aggressive growth may not require immediate treatment and can simply be monitored. Active surveillance can be an option for cancer that causes no symptoms, is confined to a small area of ​​the prostate, and is expected to grow very slowly. Treatment will only be initiated if the cancer's aggressiveness is detected and begins to pose a risk to the patient's life. However, closely monitoring these types of tumors does not mean 'doing nothing.' First, a complete prostate mapping is necessary, ensuring that no high-risk tumors are present, and the patient must understand the pros and cons of this strategy. Second, the monitoring of men in this situation is very thorough, using prostate MRIs and follow-up biopsies, in addition to highly specialized urologists in uro-oncology.

The main benefit is the absence of side effects. Among the disadvantages is the fact that patients have to undergo many tests, some of them invasive, such as prostate biopsies.

Tumors with a good prognosis that can be treated locally:

Focal Therapy

Some tumors with a good prognosis can be treated locally without the need to remove the entire prostate. The treatment used for this is focal therapy , which allows treatment of only the lesion while preserving the prostate, substantially improving the postoperative period and reducing treatment side effects.

It is a technique performed in an operating room, which destroys prostate tissue with cold or heat and can be applied in specific cases of single tumors:

  • Cryotherapy. Cryotherapy, or cryoablation, uses very low temperatures to destroy cancer cells. Needles inserted transperineally into the treatment area freeze the targeted area of ​​the prostate, destroying all tumor tissue.
  • HIFU. High-intensity focused ultrasound achieves the same damaging effect on tumorous areas, but thanks to the heat that an ultrasound device is able to concentrate in the prostate tissue and cause it to die, without affecting other adjacent tissues.
  • Electroporation. Electroporation also allows for maximum preservation of healthy structures surrounding the tumor being treated. Several needles are inserted transperineally, creating an electrical potential difference between them. This delivers a series of short, high-voltage electrical pulses that selectively destructively target the cancerous cells in the lesion.

Aggressive tumors:

Radical prostatectomy (surgery)

In cases where the tumor is aggressive and conservative treatment is not possible , surgery is the most curative option. Surgical treatment, or prostate cancer surgery, involves the complete removal of the prostate gland and surrounding tissues, and in some cases, the removal of lymph nodes in the pelvic area. It is an option for treating cancer that is confined to the prostate. Sometimes, surgery is recommended in combination with other treatments for advanced prostate cancer.

It can be done through several approaches such as:

  • Open. In open surgery or retropubic surgery, the surgeon makes a long incision in the lower abdomen to access the prostate gland and remove it.
  • LaparoscopicIn the laparoscopic approach, the surgeon makes small incisions through which surgical instruments and a video camera (laparoscope) are inserted to observe inside the abdomen during the procedure.
  • Robotic. During a robot-assisted radical prostatectomy, surgical instruments are attached to a mechanical device (robot) and inserted into the abdomen through several incisions. The surgeon sits at a console and uses hand controls to guide the robot and move the instruments.

Currently, at ROC Clinic, we have both available robotic systems: da Vinci (from Intuitive Surgical) and Toumai (from MicroPort® MedBot™ ), making us the first center in Spain to incorporate the latter. Robotic technology translates the surgeon's movements, improving ergonomics and reducing tremor. Furthermore, it allows for a true three-dimensional view of the surgical field with high-quality images that guarantee clarity and precision of detail.

However, none of the aforementioned approaches has proven superior to the others in terms of cancer control and better preservation of the patient's urinary or sexual function. While it is true that both laparoscopic and robotic surgery have been shown to reduce bleeding and the patient's hospital stay.

These procedures last approximately 2 to 4 hours and are performed under general anesthesia.

Radiotherapy

Radiation therapy is the administration of ionizing radiation to treat cancer, as it uses high-powered energy to destroy cancer cells. Radiation therapy treatments can be given alone or in combination with surgery.

In the case of prostate cancer, there is a treatment called brachytherapy, indicated only for patients with low-risk tumors, which involves inserting radioactive seeds into the prostate gland. These seeds deliver a low dose of radiation over a prolonged period.

External beam radiation therapy can also be administered using machines. This is an option for treating cancer that is limited to the prostate and can help slow the growth of prostate tumors that spread to other areas of the body, such as the bones, and relieve symptoms, such as pain. In external beam radiation therapy, the patient lies on a table while a machine moves around their body, directing high-powered energy beams (X-rays or protons) at the prostate cancer.

Hormonal Therapy

Testosterone (the male sex hormone) is directly related to the progression of prostate cancer. Hormone therapy is used to reduce testosterone levels in the body or to block its effects on the prostate. Suppression of this hormone leads to tumor regression.

Hormone deprivation therapy is usually indicated in conjunction with radiotherapy or when the disease is widespread.

How to choose the right treatment?

Every diagnosis is unique. Choosing the right treatment for prostate cancer depends on several factors that must be evaluated individually by a specialized medical team. There is no single option that works for all patients. Our specialists will comprehensively assess your case and explain the available options, benefits, and potential side effects.

FAQ

Prostate cancer in its early stages often presents no symptoms, so the only way to detect it early is through medical checkups. The main tests are the PSA blood test and a digital rectal exam. In advanced stages, symptoms such as difficulty urinating, increased urinary frequency, blood in the urine, or bone pain may appear. If you are over 50, or have a family history of prostate cancer, it is advisable to see a urologist even if you are not experiencing any discomfort.
Prostate cancer is curable, especially when detected in its early stages. If the tumor is localized, cure rates exceed 90% with treatments such as surgery, focal therapy, or radiation therapy. In advanced cases, although not curable, there are highly effective therapies that allow it to be controlled for years. Early detection is crucial to increasing the chances of a cure. Therefore, regular urological checkups are recommended starting at age 50 (or earlier if there is a family history).
La robotic operation It is recommended in a variety of situations where its advantages can significantly improve patient outcomes compared to traditional open or laparoscopic surgery. It is considered especially beneficial in complex procedures requiring high precision and surgical dexterity in confined spaces, in patients with comorbidities, and/or when preserving urinary or erectile function is desired.
It is normal to bleed for one to two weeks after a prostate biopsy, depending on the type of bleeding. There may be blood in the urine, stool, and/or semen.
At age 50, it's recommended to have a PSA test, a blood test that measures Prostate-Specific Antigen, which helps detect potential prostate abnormalities. If there's a family history of breast or prostate cancer, it's recommended to begin screening around age 45 due to the increased risk associated with developing prostate cancer.
A PSA test and a digital rectal exam are usually sufficient – ​​especially if the PSA level is above 2,5. In some cases, ultrasound, uroflowmetry, or even genetic testing may be performed to study different aspects of the prostate.
It's normal to be scared, but we have many options for achieving a cure. Localized prostate cancer refers to cancer confined to the prostate gland, with no evidence of spread to other parts of the body. This stage offers various treatment options with a high probability of cure. Depending on the characteristics of the tumor, we can consider focal therapy, prostatectomy, or radiation therapy. It's important to carefully weigh the pros and cons of each treatment and develop a personalized therapy plan. Most men with early diagnosis and appropriate treatment can expect a complete cure.
The most common complications are erectile dysfunction and urinary incontinence. It is especially important that the surgeon be highly experienced to ensure they can preserve the nerves responsible for erections, as this has been linked to improved erection and continence. The onset and duration of these complications depend on factors such as the type of surgery performed, the technique used, and each patient's individual characteristics. It is essential to follow medical instructions and attend follow-up appointments to ensure optimal recovery.
Yes. An elevated PSA level does not always indicate prostate cancer. It is very common for some men to have high PSA levels, and for these levels to increase with age without any significant abnormality being detected. Some men, on the other hand, simply have high PSA levels because they have an enlarged prostate. Therefore, there is no need to be alarmed by an elevated PSA level without a clear diagnosis. Even so, it is advisable to have regular PSA tests to monitor its changes over time.
Talk to your urologist. The best option would likely be to have a prostate MRI to rule out any problems.

Our centers
urology

We treat our patients at the ROC Chamberí clinic and in the HM Hospitals network of centers in Madrid: Sanchinarro, Montepríncipe, Madrid Río, Rivas, Puerta del Sur, Nuevo Belén, Policlínico HM Moraleja and Nuevo Norte. 

ROC Chamberí

Coming soon

ROC Bernabéu

ROC HM Sanchinarro

ROC HM Montepríncipe

ROC HM South Gate

ROC HM Madrid Río

ROC HM Rivas

ROC HM New Bethlehem

ROC HM New North

ROC Polyclinic HM Moraleja

Our centers
urology

We treat our patients at the ROC Chamberí clinic and in the HM Hospitals network of centers in Madrid: Sanchinarro, Montepríncipe, Madrid Río, Rivas, Puerta del Sur, Nuevo Belén, Policlínico HM Moraleja and Nuevo Norte. 

ROC Clinic

Urology in Madrid

4,8 ★ ★ ★ ★ ★★ ★ ★ ★ ★
make an appointment now
★ ★ ★ ★ ★★ ★ ★ ★ ★ Verified rating

We left very happy with the doctor-patient relationship

JG August 6, 2026

View all ratings (43)
Powered by TOPDOCTORS

The experience of
our patients

Our patients' trust reflects our commitment to providing excellent, personalized, and attentive urological care. Every experience motivates us to continue improving and offering the care and support each patient needs.


4,7
★★★★★ 94 reviews published in Google
Leave us a review on Google

Related articles

Can benign prostatic hyperplasia increase PSA levels?

Benign prostatic hyperplasia (BPH) can increase PSA levels without necessarily indicating prostate cancer. There is no set value...

Prostate cancer: preventing, detecting early and treating better

Prostate cancer is the most common tumor in men and often develops without symptoms in its early stages. Early detection, checkups...

Urinary flowmetry: what it is, how it is performed, and what information it provides

In urology, many clinical decisions are based on objective data. It is not enough to know that a patient "urinates worse" or that the stream "has lost..."