
Testicular Cancer
Testicular cancer has high cure rates thanks to early diagnosis and a good response to treatment.
Although it represents a small proportion of urological tumors, there are different types of testicular cancer, each with distinct characteristics and progression. Identifying the tumor type and its extent is key to determining the most appropriate treatment approach.
What is it?
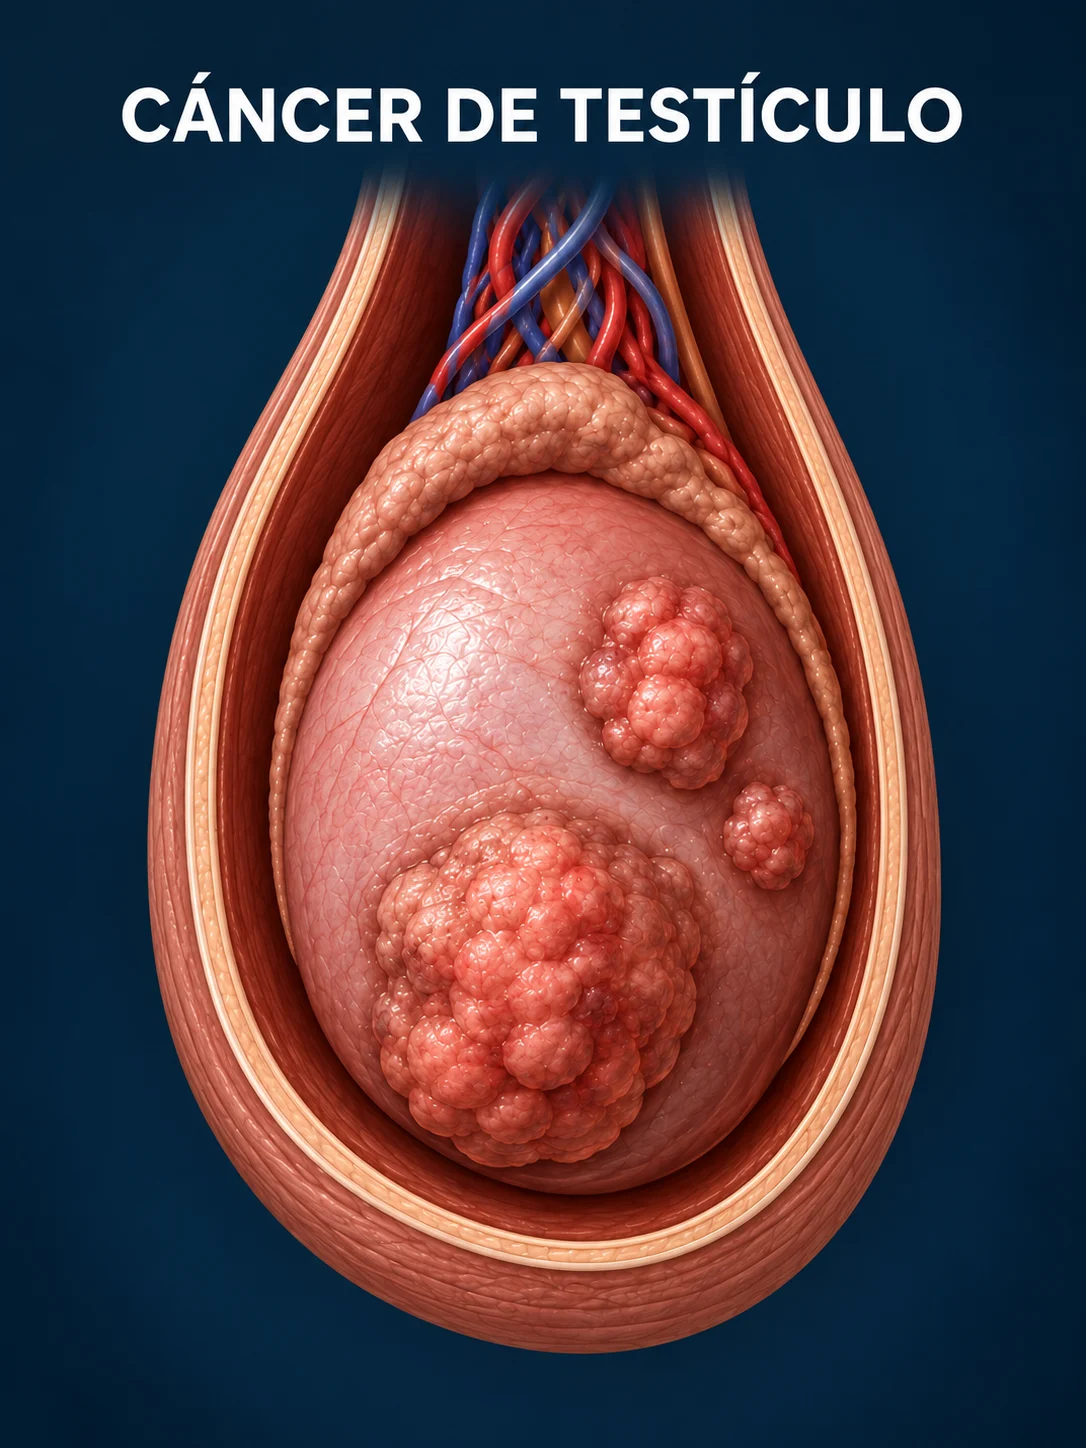
Testicular cancer occurs when cells begin to grow uncontrollably in the testicles. To understand this cancer, it is helpful to know the normal structure and function of the testicles.
The testicles are two organs of the male reproductive system located within a sac of skin called the scrotum, which hangs below the base of the penis. Their two main functions are:
- To produce male hormones (androgens), such as testosterone.
- To produce sperm, which are the male cells that fertilize the female sex cell (ovum), and thus begin a pregnancy.
Sperm cells are produced in long, thin ducts located within the testes called seminiferous tubules. These cells are stored and mature in the epididymis, a small, coiled tube located behind each testicle.
During ejaculation, sperm cells travel from the epididymis through the vas deferens to the seminal vesicles, where they mix with fluids produced by the seminal vesicles, the prostate gland, and other glands to form semen. Finally, this fluid enters the urethra (the tube inside the penis through which urine and semen pass) to be expelled from the body.
Testicular cancer typically presents as a painless, recently appearing scrotal mass. In some cases, the testicular tumor may initially be metastatic, due to local progression, retroperitoneal spread, or distant metastasis. In such cases, the symptoms will depend on the tumor's location.
There are several types of testicular tumors. Their prognosis and nature vary, and depending on their histological type, they will respond better to certain treatments.
The best initial diagnostic test is a physical examination and scrotal ultrasound. Testicular ultrasound is the gold standard and provides a great deal of information about the presence or absence of a tumor, its local impact, and invasion of neighboring organs.
If a testicular tumor is suspected based on examination or ultrasound, the next step is to perform tumor marker tests, which have diagnostic and prognostic value. These are usually performed before surgery (Beta-HCG, alpha-fetoprotein, LDH) and also during disease follow-up. In addition, it is important to order a chest and abdominal CT scan to detect the presence of lymph nodes or metastases, which testicular cancer can produce early on.
Treatment is usually performed surgically. The first step is the total or partial removal of the testicle. The former is generally preferred, although partial surgery can be performed safely provided the tumor is no larger than one-third of the testicle.
Orchiectomy is performed through an inguinal incision. The spermatic cord structures are monitored early to prevent the spread of tumor cells, and the tumor is removed. Penile prosthesis implantation may be chosen for cosmetic purposes, depending on the man's preference.
The postoperative period is usually short and benign. It is common for the patient to be discharged even on the same day as the surgery, with a follow-up appointment scheduled approximately 15 days later to discuss the biopsy results.
In cases of high-risk testicular cancer, or cancer presenting with metastasis or lymphadenopathy at the time of diagnosis, chemotherapy is generally very effective. Even in advanced cases, it is a curable disease thanks to a combination of chemotherapy and, sometimes, radiation therapy and surgery.
However, testicular tumors can recur quickly, so initial monitoring must be very intensive and thorough.
Symptom
Testicular tumors typically present as a solid, usually painless testicular nodule that can be detected through self-examination. Hemospermia (blood in the semen) is uncommon. Scrotal pain is also rare, but can occur in cases of bleeding or intratumoral ischemia.
Testicular cancer is fast-growing (within days or weeks) and usually originates in the testicle, although it can affect nearby structures. Testicular cancer metastasizes early, so it may present with symptoms caused by metastasis. For this reason, early diagnosis is crucial to prevent disease progression.
In 7% of cases, gynecomastia, or breast enlargement, occurs in men. Infertility and hypogonadism (decreased sex hormones) may also occur.
In advanced cases, general symptoms may appear, such as weight loss, loss of appetite, or lower back pain secondary to the development of a tumor mass in the retroperitoneum. This occurs because lymphatic drainage from the testicles takes place at the level of the lymph nodes surrounding the aorta and vena cava.
Causes
The incidence of testicular cancer has increased during the last few decades, especially in industrialized countries, possibly in relation to genetic disruptors (pollution, chemical agents in water and food, etc.).
In addition, several genetic alterations associated with the development of testicular tumors and multiple risk factors have been described:
- Testicular dysgenesis syndrome: Alterations in testicular development due to different causes that increase the risk of testicular cancer and cause infertility due to problems in the proper functioning of the testicle.
- Cryptorchidism: The testicles form during the embryonic stage inside the abdomen and should descend into the scrotum through the inguinal canal. This occurs between the third trimester of pregnancy and the first few months of life. The failure of the testicles to descend completely, with them remaining at different levels between the abdomen and the scrotum, is called cryptorchidism.
- Klinefelter's syndrome: A genetic disorder in which a male is born with at least one extra X chromosome (XXY). It includes, among other manifestations, hypergonadotropic hypogonadism, gynecomastia, infertility, and an increased risk of testicular cancer.
- First-degree family history of testicular tumor.
- Tumor in the other testicle.
Discovery
For the diagnosis of testicular cancer, in addition to a proper physical examination, the following diagnostic tests are performed:
- blood analysis Testicular tumor markers, which are elevated in 51% of cases, are also used to establish the prognosis and are useful for follow-up. These markers are beta-hCG, alpha-fetoprotein, and LDH. They are always measured before and after testicular removal surgery.
- Image testFor any man with a new-onset scrotal mass or pain, especially those under 40, a scrotal ultrasound is a reasonable diagnostic test. A scrotal ultrasound is the diagnostic test. gold standard for the diagnosis of scrotal pathology, and also in testicular cancer.
Doppler ultrasound allows for the study of the structure of the testicles and their blood vessels, and the determination of whether any masses are present, as well as their extent. The use of testicular ultrasound can:
- Determine whether a mass is intra- or extra-testicular.
- Determine the volume and anatomical location of the lesion.
- Characterize the contralateral testicle to exclude other lesions and identify risk factors for neoplasms.
Testicular ultrasound is also recommended for all men with retroperitoneal or visceral masses and/or without elevated testicular tumor markers in the absence of a palpable testicular mass. When there is any doubt, scrotal magnetic resonance imaging (MRI) may be performed.
- Thoraco-abdomino-pelvic CT scan. In all cases where testicular cancer has been diagnosed, a CT scan of the chest and abdomen is necessary to rule out distant metastases. In selected cases, a brain CT scan may be performed if brain metastases are suspected.
- PET. It is not used as an initial diagnostic test, but to evaluate the presence of retroperitoneal tumor despite chemotherapy treatment.
- In young patients who wish to have offspring in the future, fertility studies should be offered through semen analysis and hormonal studies (testosterone, LH and FSH) and the possibility of cryopreserving semen.
Types of testicular tumors
It is very important to classify the type of tumor after surgery, as this has significant implications for treatment and diagnosis. There are two main subgroups of testicular tumors.
Germ cell tumors:
They are the most frequent subtype (90-95% of cases) and are further classified into:
- Seminomas (35% of the total). They tend to grow and spread more slowly than non-seminomas.
- Non-seminomas (25% of the total): intratubular germ cell neoplasia, embryonal carcinoma, teratoma, teratocarcinoma, choriocarcinoma or yolk sac tumor).
- Mixed tumors (in up to 40% of cases)
Stromal cell tumors:
- Leydig cell tumor: This is the most common type of stromal tumor. It typically appears in the first decade of life or between the ages of 30 and 60. Only 10% are malignant. It is diagnosed by the presence of a painless testicular mass, gynecomastia, and hormonal abnormalities. Treatment is surgical (in some cases, breast-conserving surgery is possible), and metastatic cases show little response to chemotherapy or radiotherapy.
- Sertoli cell tumor: It typically appears around age 45. Twenty percent are malignant, but they have a low metastatic potential. It presents as a testicular mass and rarely causes gynecomastia or hormonal abnormalities. Treatment is surgical, although conservative surgery can be performed in some cases.
Treatment
Orchiectomy
The standard treatment for testicular cancer is radical orchiectomy via the inguinal route. This involves removing the testicle through an incision in the groin to avoid opening the scrotal skin and disrupting lymphatic drainage, which could lead to the spread of tumor cells. During the same surgery, a testicular prosthesis can be implanted for cosmetic purposes, which does not cause additional complications or negatively impact on cancer outcomes.
Once the testicle is removed—either partially or completely—it is sent to pathology for examination. This analysis allows us to determine the type of lesion and plan subsequent treatment. Although treatment is not usually necessary in the early stages of the disease, it is recommended for some types of tumors or if the cancer has spread beyond the testicle.
conservative surgery
Testicular-conserving surgery involves the removal of only the tumor, preserving the rest of the testicle. This procedure is only indicated for patients with tumors in both testicles or for patients with only one testicle and normal testosterone levels, provided the tumor does not occupy more than one-third of the testicular volume.
Lymphadenectomy
Retroperitoneal lymphadenectomy involves removing the metastatic lymph node mass or the lymph nodes surrounding the major blood vessels (aorta, vena cava) up to the renal arteries. An attempt should be made to preserve the ejaculatory nerves.
Chemotherapy
Testicular tumors are highly chemosensitive, so good results are obtained with chemotherapy, even in cases of metastatic disease. It is administered prophylactically after orchiectomy in high-risk patients or to treat disseminated disease.
Radiotherapy
Radiotherapy is only useful in seminomatous tumors due to their high radiosensitivity.
Following treatment, close monitoring is necessary using tumor markers, CT scans, and examination to rule out tumor recurrence.




FAQ
When is the use of robotic surgery recommended?
I've noticed a lump in my testicle, could it be a tumor?
Is testicular cancer curable?
What is the treatment for testicular cancer?
Does having a testicle removed affect my fertility?
What is a testicular prosthesis?
What if my testicular cancer has metastasized?
Our centers
urology
We treat our patients at the ROC Chamberí clinic and in the HM Hospitals network of centers in Madrid: Sanchinarro, Montepríncipe, Madrid Río, Rivas, Puerta del Sur, Nuevo Belén, Policlínico HM Moraleja and Nuevo Norte.

ROC Chamberí
- Paseo del General Martínez Campos, 17 – 1 B, 28010, Madrid
Coming soon
ROC Bernabéu
-
Basilica Street, 20, 28020,
Madrid
ROC HM Sanchinarro
- Calle de Oña, 10, 28050, Sanchinarro neighborhood, Madrid.
ROC HM Montepríncipe
- Avenida de Montepríncipe, 25, 28660, Boadilla del Monte, Madrid.
ROC HM South Gate
- Avenida de Carlos V, 70, 28938, Móstoles, Madrid
ROC HM Madrid Río
- Calle de Cobos de Segovia, 4, 28005, Arganzuela neighborhood, Madrid.
ROC HM Rivas
- Avenida de José Hierro, 94, 28521, Rivas-Vaciamadrid, Madrid.
ROC HM New Bethlehem
- José Silva Street, 7, 28043, Ciudad Lineal district, Madrid
ROC HM New North
- Calle del Marojal, 2, 28050, Las Tablas neighborhood, Fuencarral-El Pardo district, Madrid.
ROC Polyclinic HM Moraleja
- Paseo de Alcobendas, 10, 28109, Alcobendas, Madrid.
Our centers
urology
We treat our patients at the ROC Chamberí clinic and in the HM Hospitals network of centers in Madrid: Sanchinarro, Montepríncipe, Madrid Río, Rivas, Puerta del Sur, Nuevo Belén, Policlínico HM Moraleja and Nuevo Norte.
ROC Chamberí
- Paseo del General Martínez Campos, 17 – 1 B, 28010, Madrid
Coming soon
ROC Bernabéu
-
Basilica Street, 20, 28020,
Madrid
ROC HM Sanchinarro
- Calle de Oña, 10, 28050, Sanchinarro neighborhood, Madrid.
ROC HM Montepríncipe
- Avenida de Montepríncipe, 25, 28660, Boadilla del Monte, Madrid.
ROC HM South Gate
- Avenida de Carlos V, 70, 28938, Móstoles, Madrid
ROC HM Madrid Río
- Calle de Cobos de Segovia, 4, 28005, Arganzuela neighborhood, Madrid.
ROC HM Rivas
- Avenida de José Hierro, 94, 28521, Rivas-Vaciamadrid, Madrid.
ROC HM New Bethlehem
- José Silva Street, 7, 28043, Ciudad Lineal district, Madrid
ROC HM New North
- Calle del Marojal, 2, 28050, Las Tablas neighborhood, Fuencarral-El Pardo district, Madrid.
ROC Polyclinic HM Moraleja
- Paseo de Alcobendas, 10, 28109, Alcobendas, Madrid.

We left very happy with the doctor-patient relationship
JG August 6, 2026
The experience of
our patients
Our patients' trust reflects our commitment to providing excellent, personalized, and attentive urological care. Every experience motivates us to continue improving and offering the care and support each patient needs.


Excellent urological clinic due to the professionals who work there.
A highly professional clinic, with a very high scientific level and advanced technology. They helped me solve my urological problem.

I can only say one thing, the urology girls are the best you can find in this...
I want to express my gratitude to the Roc team, especially Dr. David Carracedo, for their professionalism, the...

Excellent care, both from Dr. Rojo and Dr. Espinales on a medical level and from the staff of...

Top 100 deal

I've been coming to the Urology department at HM Monteprincipe for a long time and I'm very happy with the care I receive from...
Related articles

Sexual health is an essential component of human well-being. It is not merely the absence of disease or dysfunction, but the possibility...

